Nurse practitioner job description templates by setting, plus the state practice authority map, prescriptive authority, panel targets, and credentialing.
TL;DR
Six nurse practitioner job description templates for family practice, acute care, psychiatric mental health, urgent care, specialty clinic, and telehealth roles. Each records the state practice authority tier, prescriptive authority, panel and productivity targets, and the credentialing checklist. Median NP pay was $132,300 (Bureau of Labor Statistics, May 2025). Confirm authority with your state board before posting.
The first nurse practitioner posting I ever reviewed for a small clinic was a registered nurse (RN) job description with the title swapped out. It listed vital signs, care plans, and patient education.
The posting said nothing about diagnosing, nothing about prescribing, nothing about a panel, and nothing about the collaborative agreement the state required before the hire could see a single patient. The owner could not understand why strong candidates kept passing.
A nurse practitioner (NP) is a provider. The job description has to read like a provider role: clinical authority, prescribing, panel and productivity accountability, and a credentialing path with real dates on it. Get any of those wrong and you either scare off the people you want or hire someone who legally cannot do the work you budgeted for.
At FirstHR, we build for practices that hire without a dedicated HR department, where the owner or office manager writes the posting between patients. The six templates below cover the settings where small employers actually hire NPs. Fill in the bracketed fields, confirm the rules with your state board, and post.
Ryan Howard · First week
Sign the offer letter
Sign the employee handbook
Workplace Safety course
2/3
Onboarding
Run onboarding from one checklist
Tasks, documents to sign and courses for each new hire, sent with one launch.
A nurse practitioner is an advanced practice registered nurse (APRN) who evaluates patients, diagnoses conditions, orders and interprets diagnostic tests, initiates and manages treatment, and prescribes medication. The scope is clinical decision-making, not order execution. In a small practice, an NP is a billable provider with their own patient panel.
The role is defined by a population focus rather than a job title. The APRN Consensus Model is the framework state boards of nursing work from, and it asks that education, national certification, and state licensure all align to the same population: family across the lifespan, adult-gerontology, pediatrics, neonatal, women's health, or psychiatric mental health.
A family certified NP is not interchangeable with an acute care certified NP, and hiring the wrong focus creates a licensure problem, not a training gap.
A generic job description template fails here. The document has to name the population focus, the setting, and the authority under which the NP will practice, or it describes a role that does not legally exist in your state.
Nurse Practitioner vs Registered Nurse
The difference between an NP and an RN is authority, not seniority. An RN delivers nursing care under provider orders and cannot diagnose or prescribe. An NP is the provider who writes those orders. Treating the NP role as a senior version of the RN role is the single most common mistake in these postings.
Factor
Registered Nurse (RN)
Nurse Practitioner (NP)
Core authority
Assess and deliver care under orders
Diagnose, treat, and prescribe
Credential
RN license
RN license plus APRN or NP license
Education
ADN or BSN
MSN or DNP
National exam
NCLEX-RN
Certification in a population focus
Prescribing
None
State prescriptive authority plus DEA
Billing status
Not billed as a provider
Enrolled and billed as a provider
Accountability
Care delivery and documentation
Panel, work RVUs, and outcomes
Malpractice
Employer policy, lower exposure
Individual coverage with tail
If you are hiring for care delivery under orders rather than clinical decision-making, use the nurse job description templates instead, which cover RN, licensed practical nurse (LPN), charge nurse, and certified nursing assistant (CNA) versions. If the role includes diagnosing and prescribing, you are hiring a provider and the rest of this page applies.
The distinction also matters for your other clinical hires. An NP is not a substitute for a medical assistant or an LPN, and the pay, coverage, and credentialing burden are on a different scale.
State Practice Authority: Full, Reduced, and Restricted
Nurse practitioner authority is set by state law and falls into three tiers: full, reduced, and restricted. The tier determines whether you are hiring a standalone provider or a provider plus a physician relationship you have to contract for and pay for.
According to the American Association of Nurse Practitioners (October 2026), which maintains the national map, 27 states and the District of Columbia grant full practice authority.
Full practice authority
State law lets every qualified NP evaluate, diagnose, order and interpret tests, and initiate treatment including prescribing, under the sole licensing authority of the board of nursing. You can hire an NP as a standalone provider. No physician contract to negotiate, no supervision fee, no second signature on charts. Some full authority states still require a transition period first.
Reduced practice authority
State law limits at least one element of practice. A career-long regulated collaborative agreement with another provider is required, or one element such as prescribing is restricted by setting. Budget for a written agreement and the collaborating provider time or fee that comes with it. Get the agreement signed before the start date, because the NP cannot see patients without it.
Restricted practice authority
State law requires career-long supervision, delegation, or team management by another health provider for the NP to deliver patient care at all. The delegating physician relationship is a hiring prerequisite, not paperwork. Chart review expectations, site visit frequency, and prescribing delegation are often set by state rule rather than left to the parties, so read the rule before you draft the agreement.
The map moves almost every legislative session, and several states sit between tiers by attaching an experience threshold. That is why the templates below make you record the tier and the agreement status as fields rather than assuming an answer. Four state examples show how differently these rules are written.
State example
Mechanism
What the employer has to do
Minnesota
2,080 hours under a collaborative agreement with an experienced physician or an APRN with at least three years of practice; outside primary care and mental health, the hours are served where APRNs and physicians practice together (Minn. Stat. 148.211, subds. 1c and 1d)
Confirm the hours are complete, or plan for a collaborative agreement during the transition
California
Practice without standardized procedures requires a transition of three full-time equivalent years or 4,600 hours under AB 890
Verify the attestation and the 103 or 104 category before promising independence
Florida
Autonomous registration limited to primary care, after 3,000 physician-supervised clinical hours in the five years before the request (Fla. Stat. 464.0123)
Check the registration and the specialty limit; specialty roles still need a protocol
Texas
Written physician delegation is required for the medical aspects of care, and the prescriptive authority agreement must be reviewed at least annually (Tex. Occ. Code 157.0512)
Sign and file the delegation and prescriptive authority agreement before the start date
Two primary sources are worth reading directly before you post. The Minnesota statute shows how a transition-to-practice threshold is written, and the Texas Board of Nursing explains how physician delegation works in a restricted state. Your own board of nursing is the only authority that matters for your posting.
Warning
Verify Authority Before You Write the Posting
Do not copy an authority tier from a national map into a job description. Confirm with your state board of nursing whether a written collaborative, delegation, or supervision agreement is required, whether a transition-to-practice hour threshold applies, whether the requirement differs for prescribing, and whether the setting changes the answer. In reduced and restricted states, the agreement is a condition of practice. An NP without a signed agreement cannot see patients on day one, no matter how good the offer letter looks.
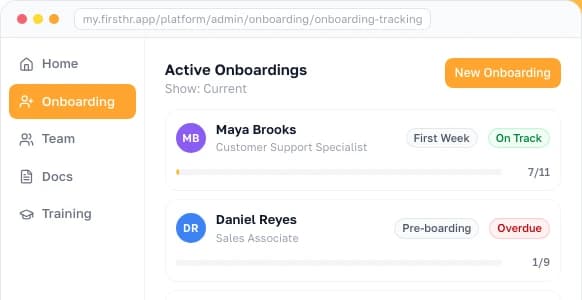
See who is on track and who is stuck
Active Onboardings lists every new hire in progress. Late items are marked, so you see them without messaging anyone.
Active OnboardingsTrack and manage employee onboarding progress#EmployeeStageProgressStatus1Angela MartinSenior AccountantStagePre-boardingProgress1/9 tasksStatusOn Track2Darryl PhilbinWarehouse ForemanStageFirst DayProgress4/10 tasksStatusOverdue3Ryan HowardSales AssociateStageFirst WeekProgress7/11 tasksStatusOn Track4Kelly KapoorCustomer Service RepresentativeStageFirst MonthProgress10/12 tasksStatusOn Track
Prescriptive Authority and DEA Registration
Prescriptive authority comes from the state, and Drug Enforcement Administration (DEA) registration only extends it to controlled substances. The order is fixed: the state authorizes prescribing, then the DEA registers the NP as a mid-level practitioner, then the prescription drug monitoring account gets opened.
Under 21 CFR 1306.03, a controlled substance prescription needs both state authorization and DEA registration, so a DEA number cannot create authority the state has not granted.
Write the prescribing scope into the description rather than assuming it. States vary on whether controlled substance schedules are included, whether a separate prescribing agreement is needed even where practice is otherwise independent, whether quantity or duration limits apply, and how often the monitoring program has to be checked. Telehealth adds a federal layer, since remote prescribing of controlled substances carries its own conditions.
1
State prescriptive authority
Granted by statute or board rule. May be independent, may require a prescribing agreement, may exclude specific schedules. This is the gate everything else passes through.
2
DEA registration
Federal registration as a mid-level practitioner for controlled substances. Available only where the state already authorizes the NP to dispense them.
3
Monitoring program account
Most states require a prescription drug monitoring program account and set the intervals at which the NP must query it before prescribing.
4
Telehealth prescribing
Remote prescribing of controlled substances is governed separately and can require an in-person evaluation. Confirm the current federal and state position.
Every template below lists prescriptive authority and DEA registration among its requirements for exactly this reason. Fill in the prescribing scope from your board rule, not from what the candidate tells you they did at their last employer in another state.
Panel and Productivity Expectations
An NP job description without productivity numbers is incomplete, because the NP is a revenue-generating provider and both sides need to know the target. Write panel size, visits per day, visit template lengths, an annual work RVU (relative value unit) goal, and a chart closure standard directly into the posting.
The economics differ from a physician hire in a way that shapes the target. Under 42 CFR 414.56, Medicare allowed amounts for nurse practitioner services may not exceed 85 percent of the physician fee schedule amount.
That 85 percent, plus your payer mix, is what turns a visit target into a revenue number, so set the target from your own schedule rather than from a benchmark you read somewhere.
Metric
What it controls
Where to set it
Attributed panel size
Continuity, access, and total workload
From your current schedule fill and no-show rate
Scheduled visits per day
Daily throughput and burnout risk
From visit template length and clinic hours
Visit template lengths
Documentation time and quality
Longer for new patients and complex intakes
Annual work RVU target
Incentive pay and the business case
From historic provider RVUs in your setting
Chart closure standard
Billing lag and compliance
Same day, next business day, or defined hours
Message and refill turnaround
Patient experience and safety
Defined hours, staffed by the care team
Review the targets at 90 days and again annually, and say so in the description. New providers ramp, panels take time to attribute, and a target written as fixed on day one gets ignored by everyone within a month.
Credentialing and Payer Enrollment
Credentialing is what turns a licensed NP into a billable provider, and it runs on a longer clock than most small employers expect. Start the day the offer is accepted, run the steps in parallel, and put the expected go-live date in writing so nobody plans a schedule around a date that cannot happen.
License and certification
Verify the RN license, the APRN or NP license, and the national certification in the exact population focus you are hiring for. Verify at the primary source, not from a PDF the candidate emails you.
Practice agreement
In reduced and restricted states, sign the collaborative, delegation, or supervision agreement before the start date and file it where a surveyor can find it.
Prescriptive authority and DEA
Confirm state prescriptive authority first, then the DEA registration, then the prescription drug monitoring account. The DEA registration follows state authority, never the other way around.
NPI, CAQH, and payer enrollment
Get the individual National Provider Identifier (NPI), complete the CAQH profile (the shared provider record that insurers draw on), and start Medicare and commercial enrollment early. Enrollment lead time is the reason a fully licensed NP can sit idle for weeks.
Privileges and competency
For hospital, surgical, or procedural settings, complete facility credentialing and delineate privileges. Keep a procedure log and competency sign-off on file.
Malpractice and renewals
Bind malpractice coverage including tail, confirm it covers every state and telehealth modality, then set renewal reminders for license, certification, DEA, and continuing medical education (CME).
Applicant tracking is coming soon to FirstHR. Until then, the practical fix for a small practice is a single checklist that every clinical hire runs through, with owners and dates attached, so a lapsed certification or a stalled payer application surfaces before it costs you a month of revenue.
Which Template Fits Your Practice?
Pick the template that matches your setting, because setting drives the population focus, the procedures, and the productivity fields. All six share the same structure. What changes is the clinical scope, the authority block, and how performance is measured.
Family Practice NP· Primary care clinic
The most common hire. Own panel, lifespan population focus, chronic disease and preventive care. Includes panel size, visit templates, and work RVU fields.
Higher acuity, admissions, rounding, and procedures under granted privileges. Requires an adult-gerontology acute care certification, not a primary care one.
Diagnostic evaluations, medication management, and therapy where in scope. Adds controlled substance prescribing and prescription drug monitoring fields.
Video and asynchronous care governed by the law of the patient state. Adds multi-state licensure, remote prescribing limits, and response time standards.
Population focus is a licensure requirement, not a preference. An acute care certified NP and a family certified NP are not interchangeable, and putting the wrong one in an inpatient or pediatric role creates a real regulatory exposure. Decide the population you serve first, then pick the template, then require the matching national certification in the posting. If your practice spans settings, hire to the primary population and define the boundary in writing.
Family Nurse Practitioner: The Most Common Small Practice Hire
A family nurse practitioner is certified for the lifespan population, which is why the FNP posting is the one most primary care practices end up writing. The description has to state the age range you actually serve, the chronic conditions the NP will manage independently, and whether pediatric patients sit on the panel or get referred out.
Two fields decide whether that posting works. Require national certification in the family population focus rather than asking for a nurse practitioner in general, and write in the panel the role will carry, because a lifespan panel with pediatric visits schedules differently from an adult-only one.
6 Nurse Practitioner Job Description Templates
Download all six as separate Word files in one ZIP, or copy individual templates below. Each includes a practice authority block, clinical responsibilities, panel and productivity fields, a credentialing checklist, and compensation with an incentive line. Fill in the brackets and confirm the authority rules with your state board before posting.
Download All 6 Job Description Templates
Family practice, acute care, psychiatric mental health, urgent care, specialty clinic, and telehealth. All as DOCX files in one ZIP.
Template 1: Family Practice Nurse Practitioner
The most common small practice hire. Lifespan population focus, own panel, chronic disease management, and preventive care. Includes panel size, visit template, and work RVU fields plus a full credentialing checklist.
Family Practice Nurse Practitioner Job Description
FAMILY PRACTICE NURSE PRACTITIONER (FNP) JOB DESCRIPTION
Employer:
Location:
Reports to: (Medical Director / Practice Owner)
Practice authority in [state]: [ ] Full [ ] Reduced [ ] Restricted
Collaborating or supervising physician: (if required)
Base salary: $ to $ per year, plus $ productivity incentive
ABOUT [EMPLOYER NAME]
[Two or three sentences about your practice, the population you serve, panel
volume, payer mix, and what makes the setting different from a hospital system.]
POSITION SUMMARY
[Employer Name] is hiring a Family Nurse Practitioner to serve as a primary care
provider for patients across the lifespan. You will carry your own patient
panel, diagnose and treat acute and chronic conditions, order and interpret
diagnostics, and prescribe within your state authority. This is an advanced
practice provider role, not a staff nursing role.
PRACTICE AUTHORITY AND CLINICAL OVERSIGHT
State practice authority:
Written collaborative or delegation agreement required: [ ] Yes [ ] No
Chart review or co-signature expectations:
Escalation pathway for complex patients:
Transition-to-practice hours required by the state, if any:
CLINICAL RESPONSIBILITIES
•Perform comprehensive histories, physical exams, and health assessments
•Diagnose and manage acute illness and chronic disease across the lifespan
•Order, perform, and interpret laboratory and imaging studies
•Prescribe medications and therapies within state prescriptive authority
•Deliver preventive care, screenings, immunizations, and counseling
•Refer to specialists and coordinate care across the medical neighborhood
•Document every encounter in the EHR and close charts within [ ] hours
•Respond to patient messages, refill requests, and results within [ ] hours
PANEL AND PRODUCTIVITY EXPECTATIONS
Target panel size: attributed patients
Scheduled patient visits per clinic day:
Visit templates: minutes new patient / minutes follow-up
Annual work RVU target:
Chart closure standard: business days
Call coverage:
These targets are reviewed at [ ] 90 days and [ ] annually.
CREDENTIALING AND LICENSURE REQUIREMENTS
•Active RN and APRN license in [state], unencumbered
•MSN or DNP from an accredited nurse practitioner program
•National certification as an FNP through a recognized certifying body
•State prescriptive authority and DEA registration where controlled
substances are prescribed
•Individual NPI, CAQH profile, and Medicare and commercial payer enrollment
•Current BLS certification; ACLS as required by setting
•Malpractice coverage: [ ] employer-provided [ ] tail coverage included
COMPENSATION AND HOW TO APPLY
Base salary: $ to $ per year
Incentive: per work RVU above or % of collections
Benefits: health, retirement, CME allowance of $, CME days,
license and certification reimbursement, malpractice coverage.
To apply, email with your resume, license number, and
national certification by .
[Employer Name] is an equal opportunity employer.
Template 2: Acute Care Nurse Practitioner
For inpatient, hospitalist, and post-acute settings. Admissions, rounding, procedures under granted privileges, and discharge planning. Requires an adult-gerontology acute care certification and facility privileging before independent shifts.
Acute Care Nurse Practitioner Job Description
ACUTE CARE NURSE PRACTITIONER (AGACNP) JOB DESCRIPTION
Employer:
Location:
Reports to: (Medical Director)
Practice authority in [state]: [ ] Full [ ] Reduced [ ] Restricted
Collaborating or supervising physician: (if required)
Employment type: [ ] Full-time [ ] Part-time [ ] Per diem
Schedule: hour shifts, per pay period, nights and weekends
Base salary: $ to $ per year plus shift differentials
POSITION SUMMARY
[Employer Name] is hiring an Acute Care Nurse Practitioner to manage complex,
higher-acuity patients in an inpatient or post-acute setting. You will admit,
round on, and discharge patients, perform bedside procedures within your
privileges, and prescribe within your state authority. Certification must match
the acute care population focus, not primary care.
Supervision, chart review, or co-signature requirements:
Escalation and rapid response expectations:
CLINICAL RESPONSIBILITIES
•Admit, evaluate, and manage patients with acute and complex conditions
•Round daily, adjust treatment plans, and lead discharge planning
•Order and interpret laboratory studies, imaging, and monitoring data
•Perform procedures within granted privileges and documented competency
•Prescribe medications within state prescriptive authority
•Communicate with families, consultants, and the interdisciplinary team
•Document admissions, progress notes, and discharge summaries in the EHR
PRODUCTIVITY AND COVERAGE EXPECTATIONS
Average daily census carried: patients
New admissions or consults per shift:
Annual work RVU target:
Discharge summary completion standard: hours
Call and cross-coverage:
CREDENTIALING AND LICENSURE REQUIREMENTS
•Active RN and APRN license in [state], unencumbered
•MSN or DNP with an adult-gerontology acute care population focus
•National certification matching the acute care population focus
•State prescriptive authority and DEA registration as applicable
•Individual NPI, CAQH profile, and payer enrollment
•BLS and ACLS current; PALS or other certifications as required
•Facility credentialing and privileging completed before independent shifts
COMPENSATION AND HOW TO APPLY
Base salary: $ to $ per year
Shift differential: $ nights, $ weekends
Benefits: health, retirement, CME allowance of $, license and
certification reimbursement, malpractice coverage with tail.
To apply, email with your resume, license number, and
national certification by .
[Employer Name] is an equal opportunity employer.
Template 3: Psychiatric Mental Health Nurse Practitioner
For behavioral health practices. Diagnostic evaluations, medication management, and therapy where in scope. Adds controlled substance prescribing, prescription drug monitoring checks, and caseload rather than panel language.
Psychiatric Mental Health Nurse Practitioner Job Description
PSYCHIATRIC MENTAL HEALTH NURSE PRACTITIONER (PMHNP) JOB DESCRIPTION
Employer:
Location:
Reports to: (Medical Director / Clinical Director)
Practice authority in [state]: [ ] Full [ ] Reduced [ ] Restricted
Collaborating or supervising psychiatrist: (if required)
For walk-in clinics. Episodic illness, minor trauma, in-clinic procedures, and disposition decisions. Adds throughput targets, solo coverage rules under state law, and written escalation and transfer criteria.
Urgent Care Nurse Practitioner Job Description
URGENT CARE NURSE PRACTITIONER JOB DESCRIPTION
Employer:
Location:
Reports to: (Site Medical Director)
Practice authority in [state]: [ ] Full [ ] Reduced [ ] Restricted
Collaborating or supervising physician: (if required)
Employment type: [ ] Full-time [ ] Part-time [ ] Per diem
Schedule: hour shifts, evenings, weekends, and holidays rotating
Base pay: $ per hour or $ to $ per year
POSITION SUMMARY
[Employer Name] is hiring a Nurse Practitioner for our urgent care clinic. You
will evaluate walk-in patients of all ages, treat episodic illness and minor
injury, perform in-clinic procedures, and decide who can go home and who needs
emergency transfer. This role rewards speed, judgment, and clean documentation.
PRACTICE AUTHORITY AND ESCALATION
State practice authority:
Written collaborative or delegation agreement required: [ ] Yes [ ] No
Solo coverage permitted under state rules: [ ] Yes [ ] No
Physician availability during shift: [ ] On site [ ] By phone [ ] Not required
Transfer and 911 escalation criteria:
CLINICAL RESPONSIBILITIES
•Evaluate and treat episodic illness, injury, and minor trauma for all ages
•Perform laceration repair, splinting, incision and drainage, and foreign body removal
•Order and interpret point-of-care testing, labs, and radiographs
•Prescribe medications within state prescriptive authority and stewardship policy
•Complete occupational health services such as physicals, drug screens, and injury care
•Decide disposition and arrange emergency transfer when indicated
•Close charts before leaving the shift
THROUGHPUT AND PRODUCTIVITY EXPECTATIONS
Patients per hour target:
Patients per shift target:
Door-to-provider time standard: minutes
Chart closure standard: end of shift
Antibiotic stewardship and satisfaction targets:
CREDENTIALING AND LICENSURE REQUIREMENTS
•Active RN and APRN license in [state], unencumbered
•MSN or DNP with a family or adult-gerontology population focus
•National certification matching the population you will treat
•State prescriptive authority and DEA registration
•Individual NPI, CAQH profile, and payer enrollment
•BLS and ACLS current; PALS preferred for pediatric volume
•Radiograph interpretation and suturing competency documented
COMPENSATION AND HOW TO APPLY
Base pay: $ per hour, or salaried at $ to $
Differentials: $ evenings, $ weekends, $ holidays
Benefits: health, retirement, CME allowance of $, malpractice coverage.
To apply, email with your resume, license number, and
national certification by .
[Employer Name] is an equal opportunity employer.
Template 5: Specialty Clinic Nurse Practitioner
For subspecialty practices. Independent clinic sessions alongside the physician, specialty diagnostics, in-office procedures, and prior authorization work. Adds procedure competency sign-off and shared panel language.
Reports to: (Physician Partner / Practice Administrator)
Practice authority in [state]: [ ] Full [ ] Reduced [ ] Restricted
Collaborating or supervising physician: (if required)
Employment type: [ ] Full-time [ ] Part-time
Base salary: $ to $ per year
POSITION SUMMARY
[Employer Name] is hiring a Nurse Practitioner for our [specialty] practice. You
will manage an established subspecialty population alongside our physicians,
run your own clinic sessions, perform specialty procedures within documented
competency, and keep patients moving between visits, testing, and treatment.
PRACTICE AUTHORITY AND SCOPE BOUNDARIES
State practice authority:
Written collaborative or delegation agreement required: [ ] Yes [ ] No
Population focus of your certification versus the specialty population:
Procedures you are credentialed to perform independently:
Procedures requiring proctoring or physician presence:
CLINICAL RESPONSIBILITIES
•Run independent clinic sessions for new, follow-up, and post-procedure patients
•Manage the subspecialty treatment plan in partnership with the physician
•Order and interpret specialty diagnostics and monitoring
•Perform in-office procedures within documented competency
•Prescribe and titrate specialty therapies within state authority
•Handle prior authorizations, appeals, and treatment coordination
•Educate patients and families on the disease course and treatment plan
PANEL AND PRODUCTIVITY EXPECTATIONS
Independent clinic sessions per week:
Scheduled visits per session:
Shared panel with physician: attributed patients
Annual work RVU target:
Procedure volume expectation:
Chart closure standard: business days
CREDENTIALING AND LICENSURE REQUIREMENTS
•Active RN and APRN license in [state], unencumbered
•MSN or DNP with a population focus appropriate to the patients you will treat
•National certification in that population focus
•State prescriptive authority and DEA registration as applicable
•Individual NPI, CAQH profile, and payer enrollment for the specialty
•Specialty certification or documented experience preferred
•Procedure log and competency sign-off maintained on file
COMPENSATION AND HOW TO APPLY
Base salary: $ to $ per year
Incentive: per work RVU above or % of collections
Benefits: health, retirement, CME allowance of $, society dues,
license and certification reimbursement, malpractice coverage.
To apply, email with your resume, license number, and
national certification by .
[Employer Name] is an equal opportunity employer.
Template 6: Telehealth Nurse Practitioner
For remote and multi-state care. Video and asynchronous visits governed by the law of the state where the patient sits. Adds multi-state licensure, remote prescribing limits, response time standards, and equipment requirements.
Telehealth Nurse Practitioner Job Description
TELEHEALTH NURSE PRACTITIONER JOB DESCRIPTION
Employer:
Work location: Remote from
States you will treat patients in:
Reports to: (Clinical Director)
Practice authority per state: [ ] Full [ ] Reduced [ ] Restricted (varies)
Collaborating or supervising physician per state: (if required)
[ ] Requires an in-person evaluation first. Confirm per state and federal rule.
Malpractice policy covers telehealth in all listed states: [ ] Yes [ ] No
CLINICAL RESPONSIBILITIES
•Conduct scheduled and on-demand video visits within your population focus
•Review asynchronous intakes and issue treatment plans within [ ] hours
•Diagnose, treat, and prescribe within the patient state authority rules
•Order labs and imaging routed to local facilities and follow up on results
•Escalate to in-person, urgent, or emergency care using written criteria
•Document every encounter in the platform and close charts within [ ] hours
•Maintain webside manner, connection quality, and patient satisfaction standards
PRODUCTIVITY EXPECTATIONS
Visits per hour target:
Visits per shift target:
Asynchronous cases per shift:
Response time standard for messages and refills: hours
Utilization and quality review cadence:
CREDENTIALING AND LICENSURE REQUIREMENTS
•Active RN and APRN license in every state where you will treat patients
•MSN or DNP and national certification in the relevant population focus
•Prescriptive authority in each state plus DEA registration where required
•Individual NPI, CAQH profile, and payer enrollment per state
•Reliable private workspace, broadband, and platform-compatible hardware
•Current BLS certification
•Compliance with HIPAA, security, and remote work policy
COMPENSATION AND HOW TO APPLY
Base pay: $ per hour, or salaried at $ to $
Licensure support: employer pays application, renewal, and CME for listed states
Benefits: health, retirement, CME allowance of $, equipment stipend,
malpractice coverage across all listed states.
To apply, email with your resume, every active license
number, and national certification by .
[Employer Name] is an equal opportunity employer.
Nurse Practitioner Salary
Anchor your range to federal wage data, then adjust for setting, specialty, geography, and call burden. Publish the range in the posting. Pay transparency is now law in a growing number of states, and NPs compare offers on total package rather than base alone.
By the numbers
Nurse Practitioner Pay and Demand
According to the Bureau of Labor Statistics Occupational Employment and Wage Statistics survey (May 2025), the median annual wage for nurse practitioners was $132,300 (BLS OEWS, 29-1171). For the combined group of nurse anesthetists, nurse midwives, and nurse practitioners, BLS reports a May 2025 median of $134,920, with the lowest 10 percent under $102,190 and the highest 10 percent above $224,490. The BLS Occupational Outlook Handbook, which carries the separate employment projections series, puts that group at about 399,000 jobs in 2025, projected to grow 36 percent from 2025 to 2035, with roughly 32,200 openings a year.
Base pay is only part of the cost. Budget for malpractice coverage with tail, a CME allowance and dedicated CME days, license and certification renewals, DEA registration, society dues, and the productivity incentive. In reduced and restricted states, add the collaborating physician arrangement, which frequently carries a monthly fee or paid chart review time and belongs in the hiring budget from the start.
Writing the Posting for a Small Practice
A small practice competes for NPs against health systems that pay more and credential faster. What a small employer can offer is scope, schedule control, and a short line to the decision-maker. Say that plainly, and back it with numbers a candidate can check.
You are hiring a provider, so the job description is a revenue document
An NP generates billable encounters. That means the posting has to state panel size, visits per day, work RVU target, and how incentive pay is calculated, because those numbers decide whether the hire pays for itself. A description that lists only clinical duties gives a candidate no way to judge the offer and gives you no basis for a performance conversation at 90 days.
Practice authority changes what you are actually buying
The same NP costs a different amount to employ depending on the state. In a restricted or reduced state you are also buying a physician relationship, chart review time, and often a monthly collaboration fee. Write the authority tier and the agreement requirement into the posting so candidates in that state know what they are signing up for and you know what to budget.
Credentialing lag is the hidden cost of the hire
Licensure, DEA, and payer enrollment run on their own clock. A practice that starts credentialing after the offer is signed can end up paying a salary for weeks before a single claim goes out. Start license verification and payer enrollment the day the offer is accepted, and put the expected go-live date in writing so nobody is surprised.
Keep the responsibilities concrete. A line such as "Manage a panel of adult patients with hypertension, diabetes, and hyperlipidemia" beats "provide high-quality patient care." Specific job responsibilities attract candidates who can do the work and filter out the ones who cannot.
Applicant tracking is coming soon to FirstHR, so for now keep applications flowing into one mailbox with a single owner and a written response time.
From Offer to First Patient
The job description becomes the offer letter, and the offer letter starts the clock on credentialing. For a provider hire, the gap between signed offer and first billable visit is the number that decides whether the hire lands well, so run onboarding and credentialing on the same timeline rather than one after the other.
1
Send the offer and agreement
Confirm title, population focus, base pay, incentive formula, and start date in writing, and prepare the collaborative or delegation agreement for signature at the same time.
2
Verify at the primary source
Check the RN license, the APRN license, the national certification and its population focus, DEA registration, and basic or advanced life support certification (BLS or ACLS) directly with the issuing body.
3
Run credentialing in parallel
NPI, CAQH, Medicare, and commercial payer enrollment all start the day the offer is accepted. Track each one with an owner and a due date.
4
Set the ramp and the review
Agree the panel and visit ramp for the first 90 days, schedule the review, and put both in the onboarding plan so the productivity target is never a surprise.
Once the offer is ready, the offer letter template handles the next step and an onboarding template gives the new provider a structured start. Both should repeat the population focus, the incentive formula, and the credentialing dates you already agreed.
Build the ramp into the onboarding plan so the first 90 days carry the same numbers the job description promised. A provider who knows the panel target and the review date on day one is a provider who can actually hit them.
FirstHR connects the offer and e-signature, an onboarding wizard and task workflows for the credentialing checklist, document management for licenses, certifications, DEA records, and signed agreements, and the HRIS to keep everything renewal-ready, so a small practice can run an onboarding workflow for a provider hire without a dedicated HR team.
FirstHR is an onboarding and HR platform, not a credentialing-verification service, billing system, or payroll provider, so connect those separately. Applicant tracking is coming soon to FirstHR.
1A nurse practitioner job description defines a provider role, so it must cover diagnosis, prescribing, panel, and productivity, not nursing tasks under orders.
2State practice authority falls into full, reduced, and restricted tiers, and the tier decides whether you also have to contract and pay for a physician relationship.
3Prescriptive authority comes from the state first; DEA registration only extends it to controlled substances where the state already allows them.
4Match national certification to the population focus and the setting, since an acute care NP and a family NP are not interchangeable.
5Write panel size, visits per day, work RVU target, and chart closure into the posting, and remember Medicare caps NP payment at 85 percent of the physician fee schedule.
6The median annual wage for nurse practitioners was $132,300 according to BLS OEWS, May 2025; budget malpractice, CME, DEA, and any collaboration fee on top.
Frequently Asked Questions
What is a nurse practitioner job description?
A nurse practitioner job description is an employer document that defines an advanced practice provider role: the population the NP will treat, the diagnoses and treatments they will manage, the prescribing they are authorized to do, the panel and productivity they are accountable for, and the licensure and credentialing they must hold. It differs from a registered nurse job description in kind, not degree. An RN description lists nursing care delivered under provider orders. An NP description defines an independent or collaborating clinician who diagnoses, orders, treats, and prescribes. Because that authority is set by state law, the description also has to record the practice authority tier and any written agreement the state requires.
What is the difference between a nurse practitioner and a registered nurse?
The core difference is authority. A nurse practitioner (NP) holds an advanced practice registered nurse (APRN) credential and can diagnose conditions, order and interpret diagnostics, start treatment, and prescribe. A registered nurse (RN) assesses patients and delivers nursing care that follows a provider’s orders, and cannot diagnose or prescribe. The credential paths differ as well. An RN earns a license through an accredited program and the NCLEX-RN exam. An NP holds that RN license plus a graduate degree, national certification in one population focus, and a separate APRN or NP license from the state. Pay, malpractice exposure, billing status, and credentialing workload all follow from that gap, so the two roles need genuinely different job descriptions and different hiring processes.
Can a nurse practitioner work without a physician?
It depends entirely on the state, and the answer sorts into three tiers. In full practice authority states, a qualified NP can evaluate, diagnose, order tests, treat, and prescribe with the board of nursing as the only licensing body, so no physician agreement is required. In reduced practice states, at least one part of practice depends on a career-long collaborative agreement with another provider. In restricted practice states, career-long supervision or delegation by another health provider is required before the NP can deliver any patient care. Some states land between tiers by requiring a transition-to-practice period first. Minnesota, for example, requires 2,080 hours under a collaborative agreement before independent practice. Check the current rule with your own state board of nursing before you post.
Do nurse practitioners have prescriptive authority?
Yes, in every state, but the terms vary. State law grants the prescriptive authority, and federal DEA registration only lets an NP prescribe controlled substances if the state already authorizes it. Some states allow full independent prescribing including controlled substances. Others require a collaborative or delegation agreement covering prescribing specifically, limit or exclude certain schedules, cap the quantity or duration of a controlled substance prescription, or require prescription drug monitoring program checks at defined intervals. Where a collaborating or supervising physician is involved, the written agreement itself can narrow the schedules the NP is permitted to prescribe. Confirm the state rule before anything else, follow it with the DEA number, finish with the monitoring program account, and note that order in your credentialing file.
What panel size and productivity should I expect from a nurse practitioner?
Set the numbers from your own schedule and payer mix, not from a national average, and write them into the job description. The fields that matter are attributed panel size, scheduled visits per clinic day, visit template lengths for new and follow-up patients, an annual work RVU (relative value unit) target, and a chart closure standard. Medicare caps its payment for NP services at 85 percent of the physician fee schedule amount (42 CFR 414.56), so the revenue model differs from a physician hire and the productivity target has to reflect that. Revisit the targets after 90 days and then every year. A posting with real numbers draws candidates who want accountability and screens out the ones who do not.
What credentials does a nurse practitioner need?
An NP needs an active RN license, an APRN or NP license in the state of practice, a master’s (MSN) or doctoral (DNP) degree from an accredited nurse practitioner program, and national certification in the population focus that matches the patients they will treat. The APRN Consensus Model names six population foci: family across the lifespan, adult-gerontology, pediatrics, neonatal, women’s health, and psychiatric mental health. Education, certification, and licensure all have to align with the same one. Before the first patient, add state prescriptive authority, DEA registration if the role involves controlled substances, an individual NPI, a CAQH profile, payer enrollment, current basic life support (BLS) certification, and malpractice coverage.
How much does a nurse practitioner cost to employ?
Wage data is the starting point, and several costs sit on top of it. The Bureau of Labor Statistics Occupational Employment and Wage Statistics survey (May 2025) reports a median annual wage of $132,300 for nurse practitioners. Beyond base pay, plan for malpractice insurance with tail coverage, a continuing medical education (CME) allowance with paid CME days, license, certification, and DEA fees, professional society dues, and any incentive tied to productivity. In reduced and restricted practice states there is one more line: the collaborating physician, often paid through a monthly fee or reimbursed chart review hours. Then count the credentialing gap. An NP who is fully licensed but not yet enrolled with payers is a salary with no billable revenue behind it.
How long does nurse practitioner credentialing take?
Several processes run at once, each on its own timeline, so begin all of them when the candidate accepts the offer. State licensure by endorsement, DEA registration, individual NPI issuance, CAQH profile completion, Medicare enrollment, and commercial payer enrollment move independently, and commercial payers are usually the slowest. For a small practice, that leaves a window where the NP is employed and licensed but cannot yet bill under their own number. Decide ahead of time how to handle it: work under a supervising provider during the window, push back the start date, or absorb the cost. Then state the expected go-live date in the offer letter so no one is caught off guard.
Make HR the easy part of running your business
Onboarding, e-signatures, training and core HR in one place. Up and running in 5 minutes.